
PHYSIO CURE · PATIENT INFORMATION
A broken shoulder can make dressing, sleeping and reaching difficult. Rehabilitation balances protecting the healing bone with gradually restoring movement and confidence. Your fracture pattern, treatment and follow-up findings determine what is safe, rather than a fixed exercise timetable.
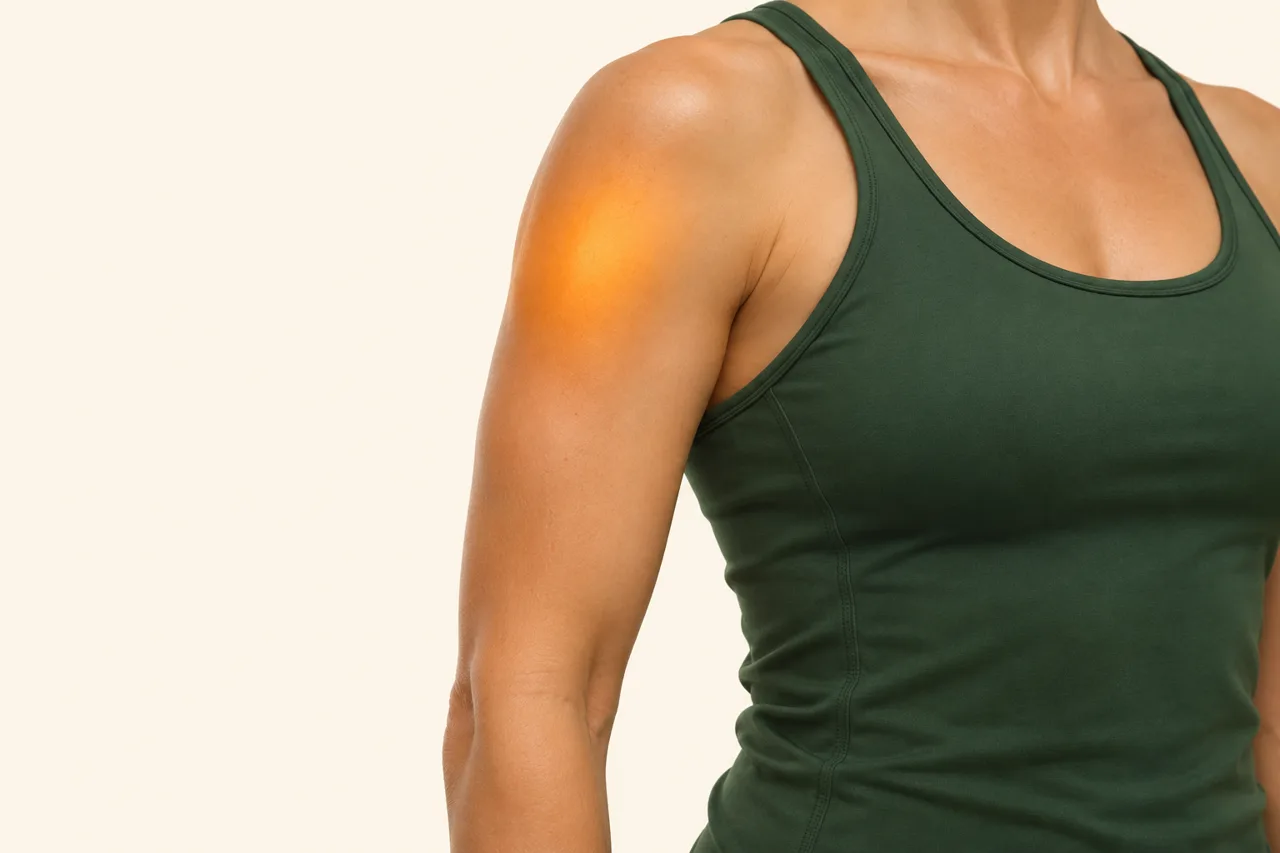
What is a proximal humerus fracture
It is a break near the top of the upper-arm bone, where the ball of the shoulder joint sits. It commonly follows a fall onto the shoulder or an outstretched hand. Older age, osteoporosis and falls increase risk. Pain, swelling, bruising and difficulty lifting the arm are typical. [1]
Assessment comes before exercises
A suspected fracture needs prompt medical assessment and usually X-rays. A physiotherapy examination alone cannot rule it out or confirm bone healing. When suspicion remains despite inconclusive X-rays, the medical team may arrange CT or MRI. [2]
After diagnosis, your physiotherapist checks the fracture-clinic or surgical instructions, pain, swelling, sensation, daily activities and permitted movement. Strength testing waits until appropriate. Follow-up appointments and any requested imaging remain important even if symptoms improve.
Other injuries can resemble or accompany a fracture: shoulder dislocation, collarbone or shoulder-blade fracture, an acromioclavicular joint injury, or a traumatic rotator-cuff tear. Persistent weakness or an unexpected recovery pattern warrants reassessment rather than simply increasing exercises. [2]
- STEP 1Confirm and protectFollow the fracture team’s instructions
- STEP 2Move when clearedRestore allowed movement gradually
- STEP 3Rebuild functionStrength and tasks as healing allows
Physiotherapy follows your healing plan
Many fractures are managed without surgery, but some need fixation or shoulder replacement. The orthopaedic team decides this with you. Rehabilitation may include:
- Protection and everyday comfort: advice on prescribed sling use, supported sleeping and adapting dressing or personal care.
- Allowed movement: hand, wrist and elbow movement, followed by gentle assisted and active shoulder movement when cleared. Avoid forceful stretching or manipulation of a healing fracture.
- Rebuilding function: gradual shoulder and arm strengthening, then practice for household tasks, work and recreation once healing and restrictions allow.
- Preventing another injury: balance and falls assessment where relevant, plus GP review of bone health after a low-trauma fracture. [1] [3]
After surgery, restrictions may also protect repaired tendons and other tissues. Do not copy someone else's programme or begin lifting, pushing or weight-bearing through the arm without clearance. Published rehabilitation schedules vary considerably. [3]
Does starting earlier help
A 2025 review of six trials found that starting movement within one week, rather than after three to four weeks, offered a small short-term functional advantage for selected non-surgical fractures. The difference was below the review's threshold for clinical importance, with no clear longer-term advantage. Complications were not significantly different, but estimates were imprecise and individual fracture types could not be assessed separately. This is not permission to start early without your treating team's agreement. [4]
More appointments are not automatically better. A 2026 trial in 60 adults aged 60 or older with displaced fractures managed without surgery found similar patient-reported outcomes with supervised rehabilitation or one advice session. Both groups retained fracture follow-up. The level of support should match your needs; these findings do not cover every fracture or postoperative patient. [5]
When to seek help
Go to an emergency department for a cold or pale hand, new significant numbness or weakness, an open wound over the injury, or marked deformity after trauma. Contact your treating team urgently for increasing wound redness or discharge, or fever after surgery. [1] [6]
Arrange review for worsening pain or stalled progress. Recovery varies, and some stiffness may remain. This guide provides general education, draws on selected evidence and does not cover every study or replace individual medical advice.
Selected sources
Sources checked 5 November 2026. A focused evidence selection, not an exhaustive review.
- Proximal humerus fractures
- ACR Appropriateness Criteria Acute Shoulder Pain: 2024 Update
- Rehabilitation protocols in proximal humerus fracture management: A systematic review
- Early versus delayed mobilisation for non-surgically treated proximal humerus fractures: a systematic review and meta-analysis of randomised trials
- Supervised rehabilitation comparable to single advice session after nonoperative treatment of displaced proximal humerus fracture: a randomized controlled trial
- Monitoring Surgical Wounds for Infection
Original educational illustrations. General information, not an individual diagnosis or treatment prescription.